


Page 24 - JSOM Winter 2025
P. 24
The pressure was observed until it reached 0mmHg or it   through the  Texas State  Anatomical Board (Texas Funeral
          stopped changing for 60s. The 60-second observation period   Commission) and the University of  Texas Southwestern
          was not included in the measurement of tPTX decompression   (UTSW)  Willed Body Program for research and procedural
          time; however, it was assumed that once pressure plateaued for   training. This study was conducted in strict accordance with
          60s, any further delay would have no additional clinical signif-  ethical guidelines governing the use of human cadaveric tis-
          icance. A closed stopcock was then placed on the established   sues. All procedures complied with the ethical standards set
          catheter, and the tPTX was redeveloped to a target pressure of   forth by the U.S. Army for research involving human remains.
          15mmHg for a subsequent procedure to be performed at the
          alternate location.
                                                             Results
          Study Population                                   The baseline demographics of the cadavers are presented in
          This study was conducted at the Center for Emergency Health   Table 1. The mean age of cadavers at death was 84 years (SD
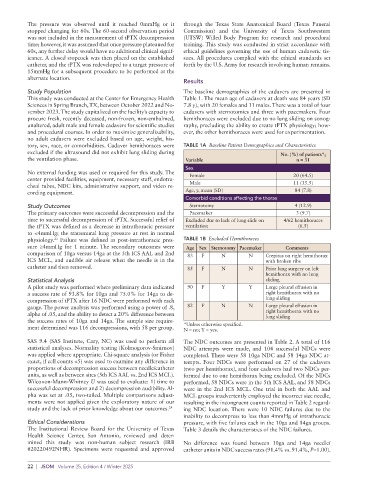
          Sciences in Spring Branch, TX, between October 2022 and No-  7.8 y), with 20 females and 11 males. There was a total of four
          vember 2023. The study capitalized on the facility’s capacity to   cadavers with sternotomies and three with pacemakers. Four
          procure fresh, recently deceased, non-frozen, non-embalmed,   hemithoraces were excluded due to no lung sliding on sonog-
          unaltered, adult male and female cadavers for scientific studies   raphy, precluding the ability to create tPTX physiology; how-
          and procedural courses. In order to maximize generalizability,   ever, the other hemithoraces were used for experimentation.
          no adult cadavers were excluded based on age, weight, his-
          tory, sex, race, or comorbidities. Cadaver hemithoraces were   TABLE 1A  Baseline Patient Demographics and Characteristics
          excluded if the ultrasound did not exhibit lung sliding during                     No. (%) of patients*;
          the ventilation phase.                              Variable                            n = 31
                                                              Sex
          No external funding was used or required for this study. The      Female               20 (64.5)
          center provided facilities, equipment, necessary staff, endotra-
          cheal tubes, NDC kits, administrative support, and video re-     Male                  11 (35.5)
          cording equipment.                                  Age, y, mean (SD)                  84 (7.8)
                                                              Comorbid conditions affecting the thorax
          Study Outcomes                                         Sternotomy                      4 (12.9)
          The primary outcomes were successful decompression and the      Pacemaker               3 (9.7)
          time to successful decompression of tPTX. Successful relief of   Excluded due to lack of lung slide on   4/62 hemithoraces
          the tPTX was defined as a decrease in intrathoracic pressure   ventilation              (6.5)
          to <4mmHg; the transmural lung pressure at rest in normal
                   23
          physiology.  Failure was defined as post-intrathoracic pres-  TABLE 1B  Excluded Hemithoraces
          sure ≥4mmHg for 1 minute. The secondary outcomes were   Age  Sex Sternotomy Pacemaker  Comments
          comparison of 10ga versus 14ga at the 5th ICS AAL and 2nd   83  F  N    N     Crepitus on right hemithorax
          ICS MCL, and audible air release when the needle is in the                    with broken ribs
          catheter and then removed.                          85   F     N        N     Prior lung surgery on left
                                                                                        hemithorax with no lung
          Statistical Analysis                                                          sliding
          A pilot study was performed where preliminary data indicated   90  F  Y  Y    Large pleural effusion in
          a success rate of 93.8% for 10ga and 75.0% for 14ga to de-                    right hemithorax with no
          compression of tPTX after 16 NDC were performed with each                     lung sliding
          gauge. The power analysis was performed using a power of .8,   82  F  N  N    Large pleural effusion in
          alpha of .05, and the ability to detect a 20% difference between              right hemithorax with no
                                                                                        lung sliding
          the success rates of 10ga and 14ga. The sample size require-
          ment determined was 116 decompressions, with 58 per group.  *Unless otherwise specified.
                                                             N = no; Y = yes.
          SAS 9.4 (SAS Institute, Cary, NC) was used to perform all   The NDC outcomes are presented in Table 2. A total of 116
          statistical analyses. Normality testing (Kolmogorov-Smirnov)   NDC attempts were made, and  104 successful NDCs were
          was applied where appropriate. Chi-square analysis (or Fisher   completed. There were 58 10ga NDC and 58 14ga NDC at-
          exact, if cell counts <5) was used to examine any difference in   tempts.  Four  NDCs  were performed  on 27  of  the cadavers
          proportions of decompression success between needle/catheter   (two per hemithorax), and four cadavers had two NDCs per-
          units, as well as between sites (5th ICS AAL vs. 2nd ICS MCL).   formed due to one hemithorax being excluded. Of the NDCs
          Wilcoxon-Mann-Whitney U was used to evaluate: 1) time to   performed, 58 NDCs were in the 5th ICS AAL, and 58 NDCs
          successful decompression and 2) decompression audibility. Al-  were in the 2nd ICS MCL. One trial in both the AAL and
          pha was set at .05, two-tailed. Multiple comparisons adjust-  MCL groups inadvertently employed the incorrect size needle,
          ments were not applied given the exploratory nature of our   resulting in the incongruent counts reported in Table 2 regard-
          study and the lack of prior knowledge about our outcomes. 24  ing NDC location. There were 10 NDC failures due to the
                                                             inability to decompress to less than 4mmHg of intrathoracic
          Ethical Considerations                             pressure, with five failures each in the 10ga and 14ga groups.
          The Institutional Review Board for the University of Texas   Table 3 details the characteristics of the NDC failures.
          Health Science Center, San  Antonio, reviewed and deter-
          mined  this study  was  non-human subject  research  (IRB   No difference was found between 10ga and 14ga needle/
          #20220492NHR). Specimens were requested and approved   catheter units in NDC success rates (91.4% vs. 91.4%, P=1.00).

          22  |  JSOM   Volume 25, Edition 4 / Winter 2025

